On this page
Why Medical Conspiracy Theories Are Uniquely Dangerous
A conspiracy theory about, say, an ancient civilisation or an unsolved historical murder can spread widely and cause minimal direct harm. Medical conspiracy theories do not have that luxury. When significant numbers of people reject effective treatments, refuse vaccinations, or delay medical care in favour of unproven alternatives, the consequences are measurable in preventable illness and death.
That is what makes the persistence of thoroughly debunked medical claims not merely intellectually interesting but genuinely consequential. Each theory examined below has been tested by large-scale studies with rigorous methodology and found to be unsupported. Each continues to circulate, attract believers, and influence health decisions. Understanding why they persist is as important as cataloguing the evidence against them, because contradiction alone has repeatedly proved insufficient.
The MMR-Autism Link: One Fraudulent Study, Millions of Converts
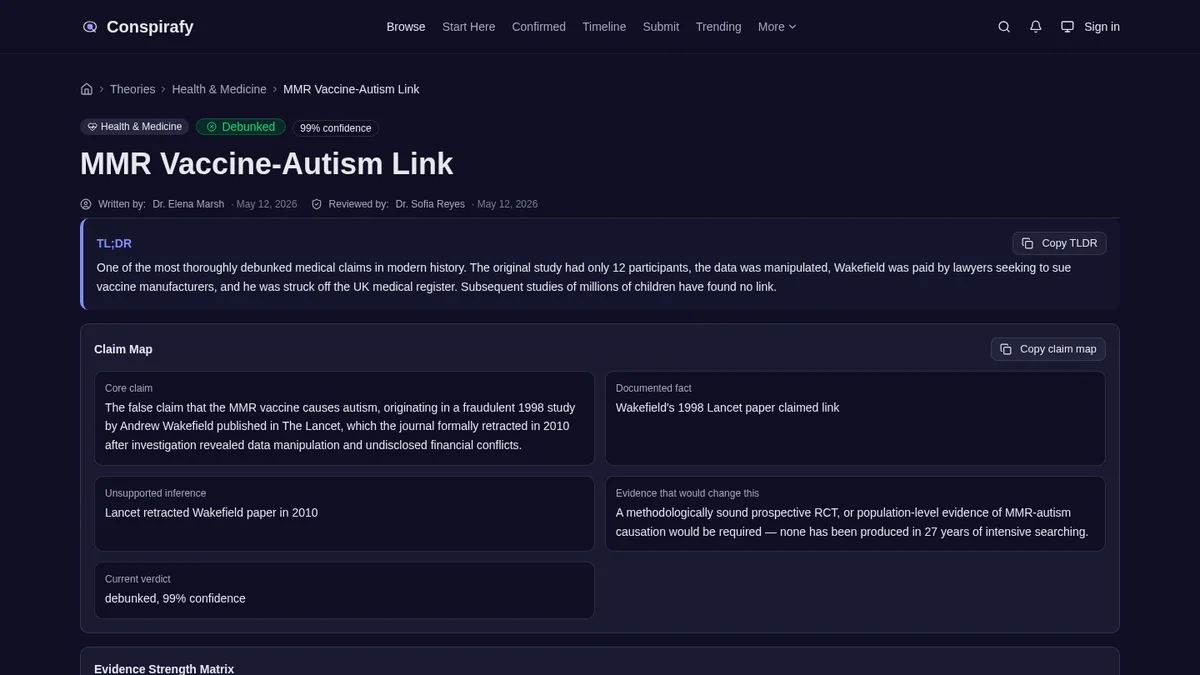
The claim that the measles-mumps-rubella vaccine causes autism traces to a single study published in The Lancet in 1998 by Andrew Wakefield and twelve co-authors. The study examined twelve children and proposed a potential link between MMR vaccination, bowel disease, and autism. It was small, speculative, and (as investigation eventually established) fraudulent.
Investigative journalist Brian Deer documented in 2004 and 2009 that Wakefield had received undisclosed payments from lawyers pursuing vaccine litigation, had falsified data in the paper, and had conducted invasive procedures on children without ethical approval. The Lancet retracted the study in full in 2010. Wakefield was struck off the medical register. The MMR-autism claim dismantled with trial evidence documents the complete deconstruction of the original study and its consequences.
In the years since, more than thirty large-scale epidemiological studies involving millions of children across multiple countries have found no link between MMR vaccination and autism. A 2019 Danish cohort study of 657,461 children, one of the largest ever conducted, found no increased autism risk. The scientific consensus is as close to unanimous as medical science gets.
Yet the claim persists, for reasons that illuminate the sociology of medical misinformation. Many parents who first encountered the Wakefield claim have integrated it into their identity and their parenting decisions in ways that make retraction psychologically difficult. The claim also benefits from the post-hoc confusion between autism diagnosis timing and vaccination timing: children typically receive MMR at approximately the age when autism symptoms become noticeable, which creates a coincidence that feels like causation even though large studies find no causal relationship.
AIDS Denialism and Its Documented Body Count
AIDS denialism (the claim that HIV does not cause AIDS, or that AIDS is caused by lifestyle factors rather than viral infection) has a longer history and a documented mortality cost. The denialist position was associated most prominently with molecular biologist Peter Duesberg, who argued through the 1980s and 1990s that AIDS was caused by recreational drug use and antiretroviral drugs rather than HIV.
The impact of this position on policy was most visible in South Africa under President Thabo Mbeki, who was influenced by denialist arguments and delayed the rollout of antiretroviral treatment programmes between 1999 and 2005. A 2008 study published in the Journal of Acquired Immune Deficiency Syndromes estimated that Mbeki's policies resulted in approximately 330,000 preventable deaths. The estimate was based on comparing South Africa's treatment outcomes to those of comparable African countries that implemented standard antiretroviral programmes.
The mechanism by which AIDS denialism spread among people without scientific training involved a rhetorical move common to other medical conspiracy theories: presenting the complexity of scientific disagreement as evidence that the mainstream consensus was suppressing legitimate alternative views. The fact that scientists debated specific aspects of HIV biology was reframed as evidence that the causal role of HIV itself was contested. It was not, in any serious scientific forum.
Ivermectin as COVID Cure: From Animal Parasiticide to Political Symbol
During the COVID-19 pandemic, ivermectin (a medication used primarily to treat parasitic infections in animals and humans) became the focus of intense public controversy. Early in vitro studies, showing that high concentrations of ivermectin could inhibit SARS-CoV-2 replication in cell cultures, were rapidly extrapolated into claims of clinical efficacy that the underlying research did not support.
Multiple large randomised controlled trials were conducted to resolve the question properly. The ACTIV-6 trial, the PRINCIPLE trial run by the UK National Health Service, and the TOGETHER trial in Brazil all enrolled thousands of participants and found no clinically meaningful benefit from ivermectin for COVID-19 treatment. Several of the earlier small studies claiming to show benefit were retracted for data fabrication.
The vaccine misinformation and false cure narratives catalogued documents the full trajectory of ivermectin claims alongside other pandemic-era treatment theories. The ivermectin episode was unusual in the speed and scale of its politicisation — the drug became a symbol of resistance to mainstream medical authority in ways that made evidential rebuttal feel like political attack to its advocates.
The Bill Gates Depopulation Claim: Anatomy of a Misquote
The claim that Bill Gates has advocated reducing world population through vaccination (framing vaccinations as a covert depopulation tool) traces to a selective misreading of a 2010 TED talk. In that talk, Gates presented a formula showing that carbon emissions are a function of population, energy use, and carbon intensity, and argued that improvements in reproductive health and child survival could stabilise population growth by reducing the number of children families needed to have to ensure some would survive.
The argument Gates was making, that child survival reduces the incentive for high birth rates, is a standard demographic transition theory supported by decades of development research. It was transformed, through selective quotation and context stripping, into a claim that Gates intended to use vaccines to reduce population. The two propositions are not merely different; they are opposites.
Examining the transformation from original statement to viral claim illustrates a pattern common to medical conspiracy theories: a real public figure, a real documented statement, and a reframing that inverts the meaning of the original.
Why Debunking Is Not Enough — and What Actually Works
Each of the theories above has been thoroughly debunked. The debunking did not kill the theory. In several cases, the debunking appeared to strengthen it, because the act of official refutation was incorporated into the conspiracy narrative itself — the debunkers became part of the cover-up.
Research into why debunking fails has identified several consistent findings. The initial exposure to a false claim often leaves a trace even after the correction is accepted intellectually: the "continued influence effect" shows that misinformation shapes reasoning even when people know it has been retracted. Additionally, corrections that simply contradict without providing an alternative explanation tend to leave an explanatory vacuum that the original claim can re-fill.
What has shown more consistent effectiveness is a combination of approaches: explaining why the false claim is compelling (and thereby reducing its unexplained appeal), providing the correct alternative framework before debunking rather than after, and addressing the identity and social function that belief in the claim is serving for the individual. None of these approaches is comfortable or quick. They require treating the person rather than the claim, a considerably harder undertaking than presenting a rebuttal study.